F- CLINICAL ASPECTS OF SPINAL CORD INJURIES
427
ON
(S
O
o
o
ON
oo
M NO NO
OO
cr\ *f
M
(SJ
oo
r^
NO
OO
NO
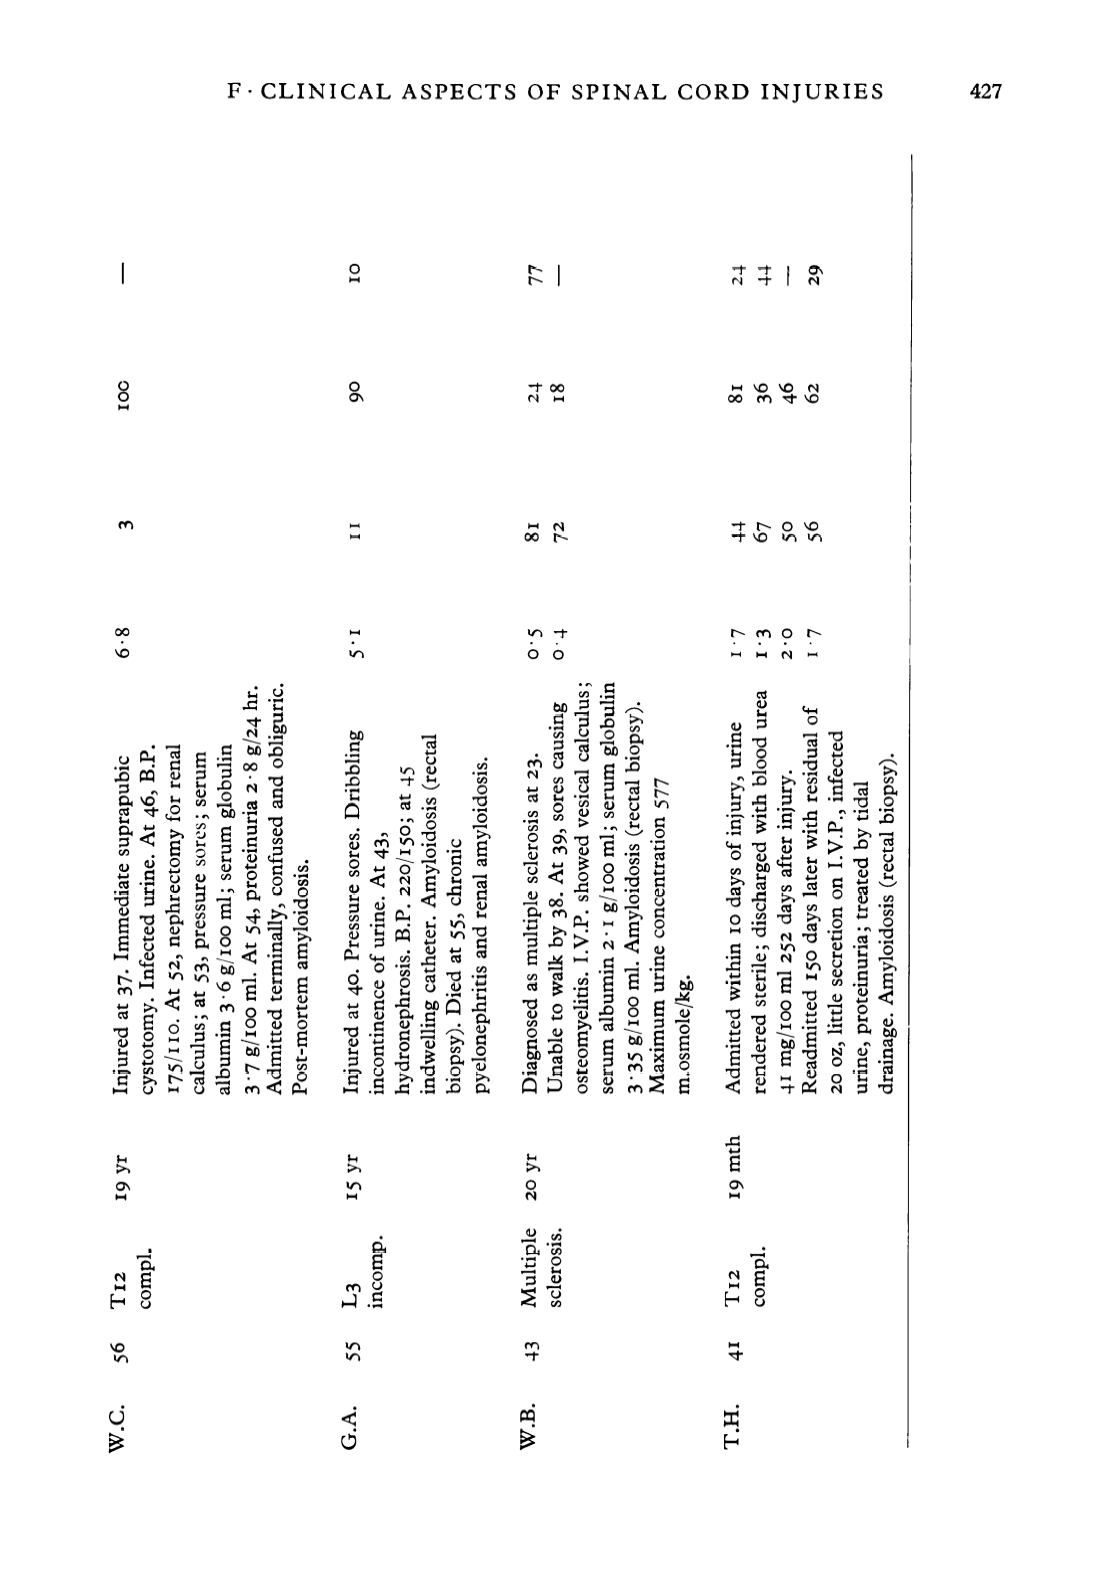
Injured
at
37.
Immediate
suprapubic
cystotomy.
Infected
urin .
At
46,
B.P
175/110.
At 2,
nephrectomy
for
renal
J-H
ON
M
"Hi
N g
H 8
NO
calculus;
at
53,
pressure
sore ;
serum
albumin
3
-6
g/ioo
ml;
serum
lob lin
n*
.0
Tj-
3
3
•7g/ioo
ml.
At
54,
proteinuria
2
•
8g/2
Admitted
terminally,
confus d
and
oblig
Post-mortem
amyl idosis.
>—i
Injured
at
40.
Pressure
sores.
Dribbling
incontinence
of
uri e.
At
43,
JH
V>
M
d
6
0
m u
H-l
.S
^•/">
hydronephrosis.
B.P.
220/150;
at4
indwelling
catheter.
Amyloidosis
(rectal
biopsy).
Died
at
55,
chronic
pyelonephritis
and
r nal
amyloidosi.
0 0
oo
00 3
c 3
Diagnosed
as
multiple
sclerosis
t23.
Unable
to
walk
by
38.
At
39,
s r s
causi
osteomyelitis.
I.V.P.
sh w d
v sical
calc
M
o
N
*H< '55
•n o
•—
«
t-i
^ ju
»^
C/3
CO
-t
a
_n
>>
serum
albumin
2•ig/ioo
ml;
serum
glo 3
'35
g/ioo
ml.
Amyloidosis
(rectal
bi ps
Maximum
urine
concentration
577
m.osmole/kg.
t^ m
I—I
M
CTJ
<M
3
Admitted
within
10
days
of
injury,
urin<
rendered
sterile;
discharged
with
blood
•M
6
ON
M
"Hi
(S
C
h 8
M^
o r^
<N
-i
0
41
mg/loo
l
252
days
after
injury.
Readmitted
150
days
l ter
with
r sdual
20
oz,
little
secretionn
I.V.P.,
inf ct d
urine,
proteinuria;
t eated
by
idal
drainage.
Amyloidosis
(rectal
biopsy)
u
O
PQ
ffi


